


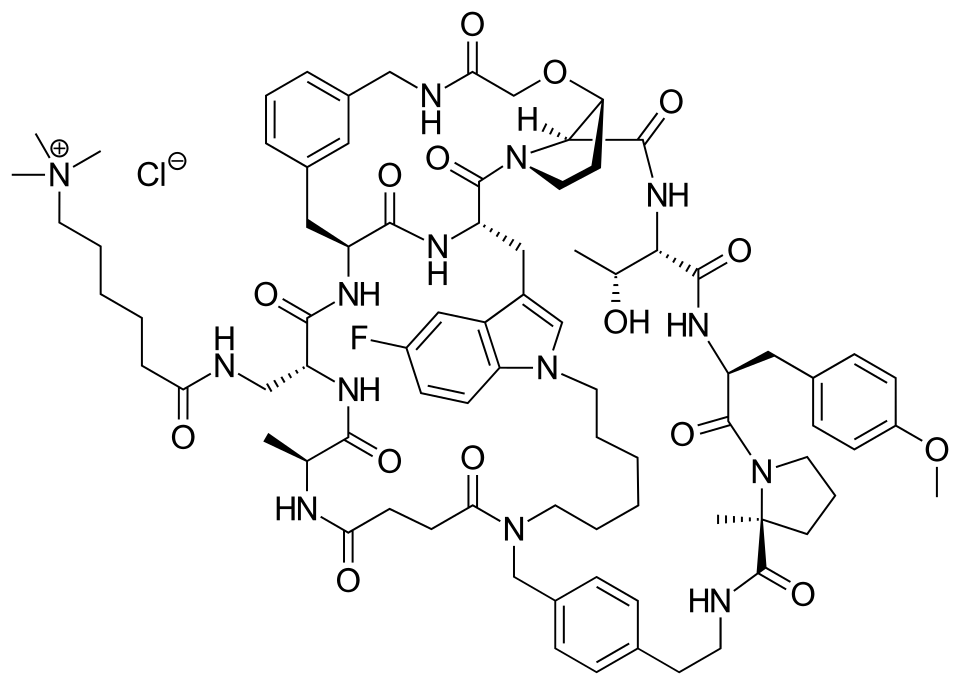
This July, the FDA approved a new cholesterol drug called Lipfendra. “What’s Lipfendra?” you may ask. Simply put, it is a pill taken once a day that blocks a protein called PCSK9, and in doing so lowers low-density lipoprotein (LDL) cholesterol by more than half.
In 2026, this approval might not seem remarkable. However, drugs in this class have existed only as injections, and creating a pill took more than a decade. What is more, in May, a separate research team published data on a gene-editing therapy that targets the same protein, needs to be given only once by intravenous (IV) infusion, and may work for a lifetime.
How PCSK9 Works, and How We Found It
A drug class, in this context, means a group of medicines that all act on the same target, in this case PCSK9, regardless of how they are built or how they get into the body. The reason this drug class was limited to injections for so long comes down to physical shape. Most pills work by fitting into a groove on the surface of their target protein, the way a key fits a lock. PCSK9 has no groove. It works across a wide, flat patch. A molecule small enough to survive digestion is far too small to cover a patch that size and anything large enough gets torn apart by stomach acid before it ever reaches the bloodstream. So for years, the only way around this problem was to skip digestion entirely: through injection.
Liver cells pull LDL cholesterol out of your blood using LDL receptors. The receptor grabs an LDL particle, drags it inside the cell, drops it off, and then goes back to the surface to do it again. This recycling is the important takeaway here. A single receptor usually handles many particles over its lifetime. PCSK9 breaks this recycling in a process called PCSK9-mediated lysosomal degradation. In this process, your liver secretes PCSK9 into the bloodstream, where it latches onto a specific region of the LDL receptor called the Epidermal Growth Factor-A (EGF-A) domain. That binding means that, instead of heading back to the cell surface, the receptor is sent to the lysosome and degraded. Every receptor PCSK9 touches is essentially lost, so higher PCSK9 levels mean your liver runs short on receptors, and your LDL climbs. Lower the amount of PCSK9 and the opposite happens.
Jonathan Cohen and Helen Hobbs, two geneticists at UT Southwestern Medical Center in Dallas, reasoned that if too much PCSK9 caused disease, too little might protect against it. They went looking for people with broken copies of the PCSK9 gene in the Atherosclerosis Risk in Communities cohort, a long-running federal study tracking cardiovascular health in thousands of Americans, and found them in roughly 2.6% of Black participants. Those carriers had 28% lower LDL. Over 15 years, they had 88% lower risk of coronary heart disease. A different, milder variant of this gene in white participants produced a 15% LDL reduction and 47% lower risk.
We should stop at that 88% for a second, because it doesn’t match what drugs do. Hand a 55-year-old a statin (a widely prescribed cholesterol-lowering drug) that cuts LDL by 28% and you will not cut their heart disease risk by anything close to 88%. The difference is timing. Arterial damage results from cumulative exposure that starts in childhood. Think of it as a bathtub that has been filling slowly since birth: what determines whether it overflows is not how fast the tap is running today, but how much water has collected over an entire lifetime. A statin started in middle age deals with the last stretch of that, whereas being born with a broken PCSK9 gene deals with all of it. Same reduction in flow, vastly different totals.
Then came a more extreme version of the same experiment. Two people in the medical literature turned out to have lost both copies of the gene rather than one, meaning they produced essentially no functional PCSK9 at all. Their LDL levels sat under 20 mg/dL, less than a quarter of what is considered normal, and they were fine. This mattered because the obvious worry about blocking any protein is that it might be doing something important nobody has thought of yet. Yet, nature had essentially already run the knockout study and showed no safety concerns.
There is also a second benefit, but whether it translates into fewer heart attacks is not yet established. Lipoprotein(a), or Lp(a), is an LDL particle with an extra protein stuck to it, and an individual’s level is genetically predetermined, meaning diet and exercise barely move it. Elevated Lp(a) raises the risk of both clogged arteries and a stiffened aortic valve. Statins do not lower Lp(a) and, if anything, they raise it slightly. PCSK9 antibodies lower it by about 27% in clinical trials.
But that still leaves the question, does moving the LDL level keep people alive?
The first answer came in 2017, when researchers found that PCSK9-inhibiting drugs prevent second heart attacks in people who already had one. However, those patients were already sick and being watched. The harder question is whether we should be treating people before anything goes wrong.
That answer arrived last November from a publication in the New England Journal of Medicine. The study enrolled 12,257 high-risk adults with atherosclerosis or diabetes who had never had a heart attack or stroke and followed them for about four and a half years. The patients on evolocumab, a PCSK9 inhibitor, had fewer cardiovascular events. It was the first time a drug in this class was shown to prevent a first heart attack rather than a second.
These findings shifted the cholesterol guidelines. The major American cholesterol guideline was rewritten this year, and it promoted these drugs from a fallback to a first choice for certain high-risk patients. It also now advises doctors to measure Lp(a) at least once in every adult, a practice that was not common just five years ago.
The Delivery Problem
The next step was figuring out the route of administration, and the results of the past few years have been intriguing. Three approaches have emerged, each stranger than the last.
Inclisiran, the first of the three, is a piece of RNA that intercepts the liver’s instructions for building PCSK9, stopping the protein before it is produced. Second came enlicitide, sold as Lipfendra, the newly approved pill and the answer to the flat-surface problem described earlier. Merck, the pharmaceutical company that developed it, built a ring-shaped molecule large enough to blanket that whole surface and chemically reinforced it to survive stomach acid. In its main trial it cut LDL by about 56% and outperformed existing oral options.
There is also VERVE-102, which some researchers do not even consider a drug, at least in the traditional sense. It is a single IV infusion that delivers a gene-editing tool into liver cells and rewrites one letter of the PCSK9 gene so that it no longer produces working protein. In early results from 35 patients, published in May, the highest dose lowered PCSK9 by an average of 88% and LDL by an average of 62%. The effects held up to 18 months of follow-up.
Why Any of This Matters
Most Davidson students will never be prescribed any of this, and that is rather the point. The cumulative exposure finding is the part that matters, because it means the buildup has already started. Plaque does not wait for a diagnosis or for anyone to turn 40. Whatever your LDL is during college is already being added to a lifetime total, and that total is what this research consistently shows matters most.
That does not mean acting on it now, at least not with medication. It does mean knowing two things. The first is that a lipid panel is a routine blood test, available through the Student Health Center or at any physician back home over break, and for most people in their twenties, LDL is a number worth knowing. The second is more specific. Lp(a) is genetic, does not respond to how you eat or train, and current guidelines now recommend testing it once in every adult. If anyone in your family had a heart attack or stroke unusually young, particularly before 50, that is worth raising with a physician, since familial hypercholesterolemia affects roughly one in 250 people and most of them have no idea they have it.
Gene editing is permanent, which is both the appeal and the risk. Lipfendra, meanwhile, was approved on the strength of cholesterol numbers rather than proof that it prevents heart attacks, and that data is still years away. Cost has kept this entire class out of reach for many people since 2015, and a pill does not automatically fix that.
Even so, PCSK9 went from an almost unheard-of gene in 2002 to an injection in 2015, a pill just this summer, and it is now being switched off in people’s livers with a single infusion. Cardiology has spent a century treating cholesterol as a chore that needs to be managed forever. The families this all started with never had to manage anything; they were simply born with the protection. Twenty years later, the field has finally worked out how to hand it to everyone else.
Works Cited
Merck & Co. “Merck’s LIPFENDRA (enlicitide) is the First and Only Once-Daily Oral PCSK9 Inhibitor Approved by the U.S. FDA to Reduce LDL-C in Adults with Hypercholesterolemia.” Press release, 16 July 2026. https://www.merck.com/news/mercks-lipfendra-enlicitide-is-the-first-and-only-once-daily-oral-pcsk9-inhibitor-approved-by-the-u-s-fda-to-reduce-ldl-c-in-adults-with-hypercholesterolemia/
Vafai, Scott B., et al. “In Vivo Base Editing of PCSK9 with VERVE-102 for Hypercholesterolemia.” New England Journal of Medicine, published online 25 May 2026. doi:10.1056/NEJMoa2601283
Seidah, Nabil G., and Annik Prat. “The Multifaceted Biology of PCSK9.” Endocrine Reviews, vol. 43, no. 3, 2022, pp. 558-582. doi:10.1210/endrev/bnab035
Cohen, Jonathan C., Eric Boerwinkle, Thomas H. Mosley Jr., and Helen H. Hobbs. “Sequence Variations in PCSK9, Low LDL, and Protection against Coronary Heart Disease.” New England Journal of Medicine, vol. 354, no. 12, 23 Mar. 2006, pp. 1264-1272. doi:10.1056/NEJMoa054013
Zhao, Zhenze, et al. “Molecular Characterization of Loss-of-Function Mutations in PCSK9 and Identification of a Compound Heterozygote.” American Journal of Human Genetics, vol. 79, no. 3, 2006, pp. 514-523. doi:10.1086/507488
Blumenthal, Roger S., Pamela B. Morris, Mario Gaudino, et al. “2026 ACC/AHA/AACVPR/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA Guideline on the Management of Dyslipidemia.” Journal of the American College of Cardiology, vol. 87, no. 19, 19 May 2026, pp. 2624-2757. doi:10.1016/j.jacc.2025.11.016
Jaffe, Ilana Z., et al. “Impact of Proprotein Convertase Subtilisin/Kexin Type 9 Inhibitors on Lipoprotein(a): A Meta-Analysis and Meta-Regression of Randomized Controlled Trials.” JACC: Advances, 2025. doi:10.1016/j.jacadv.2024.101549
Sabatine, Marc S., Robert P. Giugliano, Anthony C. Keech, et al. “Evolocumab and Clinical Outcomes in Patients with Cardiovascular Disease.” New England Journal of Medicine, vol. 376, no. 18, 4 May 2017, pp. 1713-1722. doi:10.1056/NEJMoa1615664
Bohula, Erin A., Nicholas A. Marston, Ajay K. Bhatia, et al. “Evolocumab in Patients without a Previous Myocardial Infarction or Stroke.” New England Journal of Medicine, vol. 394, no. 2, 8 Jan. 2026, pp. 117-127. doi:10.1056/NEJMoa2514428
Ray, Kausik K., R. Scott Wright, David Kallend, et al. “Two Phase 3 Trials of Inclisiran in Patients with Elevated LDL Cholesterol.” New England Journal of Medicine, vol. 382, no. 16, 2020, pp. 1507-1519. doi:10.1056/NEJMoa1912387
Centers for Disease Control and Prevention. “About Familial Hypercholesterolemia.” CDC, 2024. https://www.cdc.gov/heart-disease-family-history/about/about-familial-hypercholesterolemia.html